Coming home from hospital: the first two weeks
Discharge is not recovery. What to put in place before the ambulance arrives, and what to watch for afterwards.

By the AnnMarie’s Care team
Published —6 min read
Updated

At a glance. Confirm the discharge plan, medicines, equipment and named contacts before the journey home. Arrange support around assessed needs and know which changes need urgent help.
Hospital discharge often moves faster than families expect. A bed is needed, someone is medically fit, and a date appears with very little notice.
Being medically fit for discharge is not the same as being safe at home, and the gap between the two is where most problems happen.
 Care Journal 03
Hospital to home England
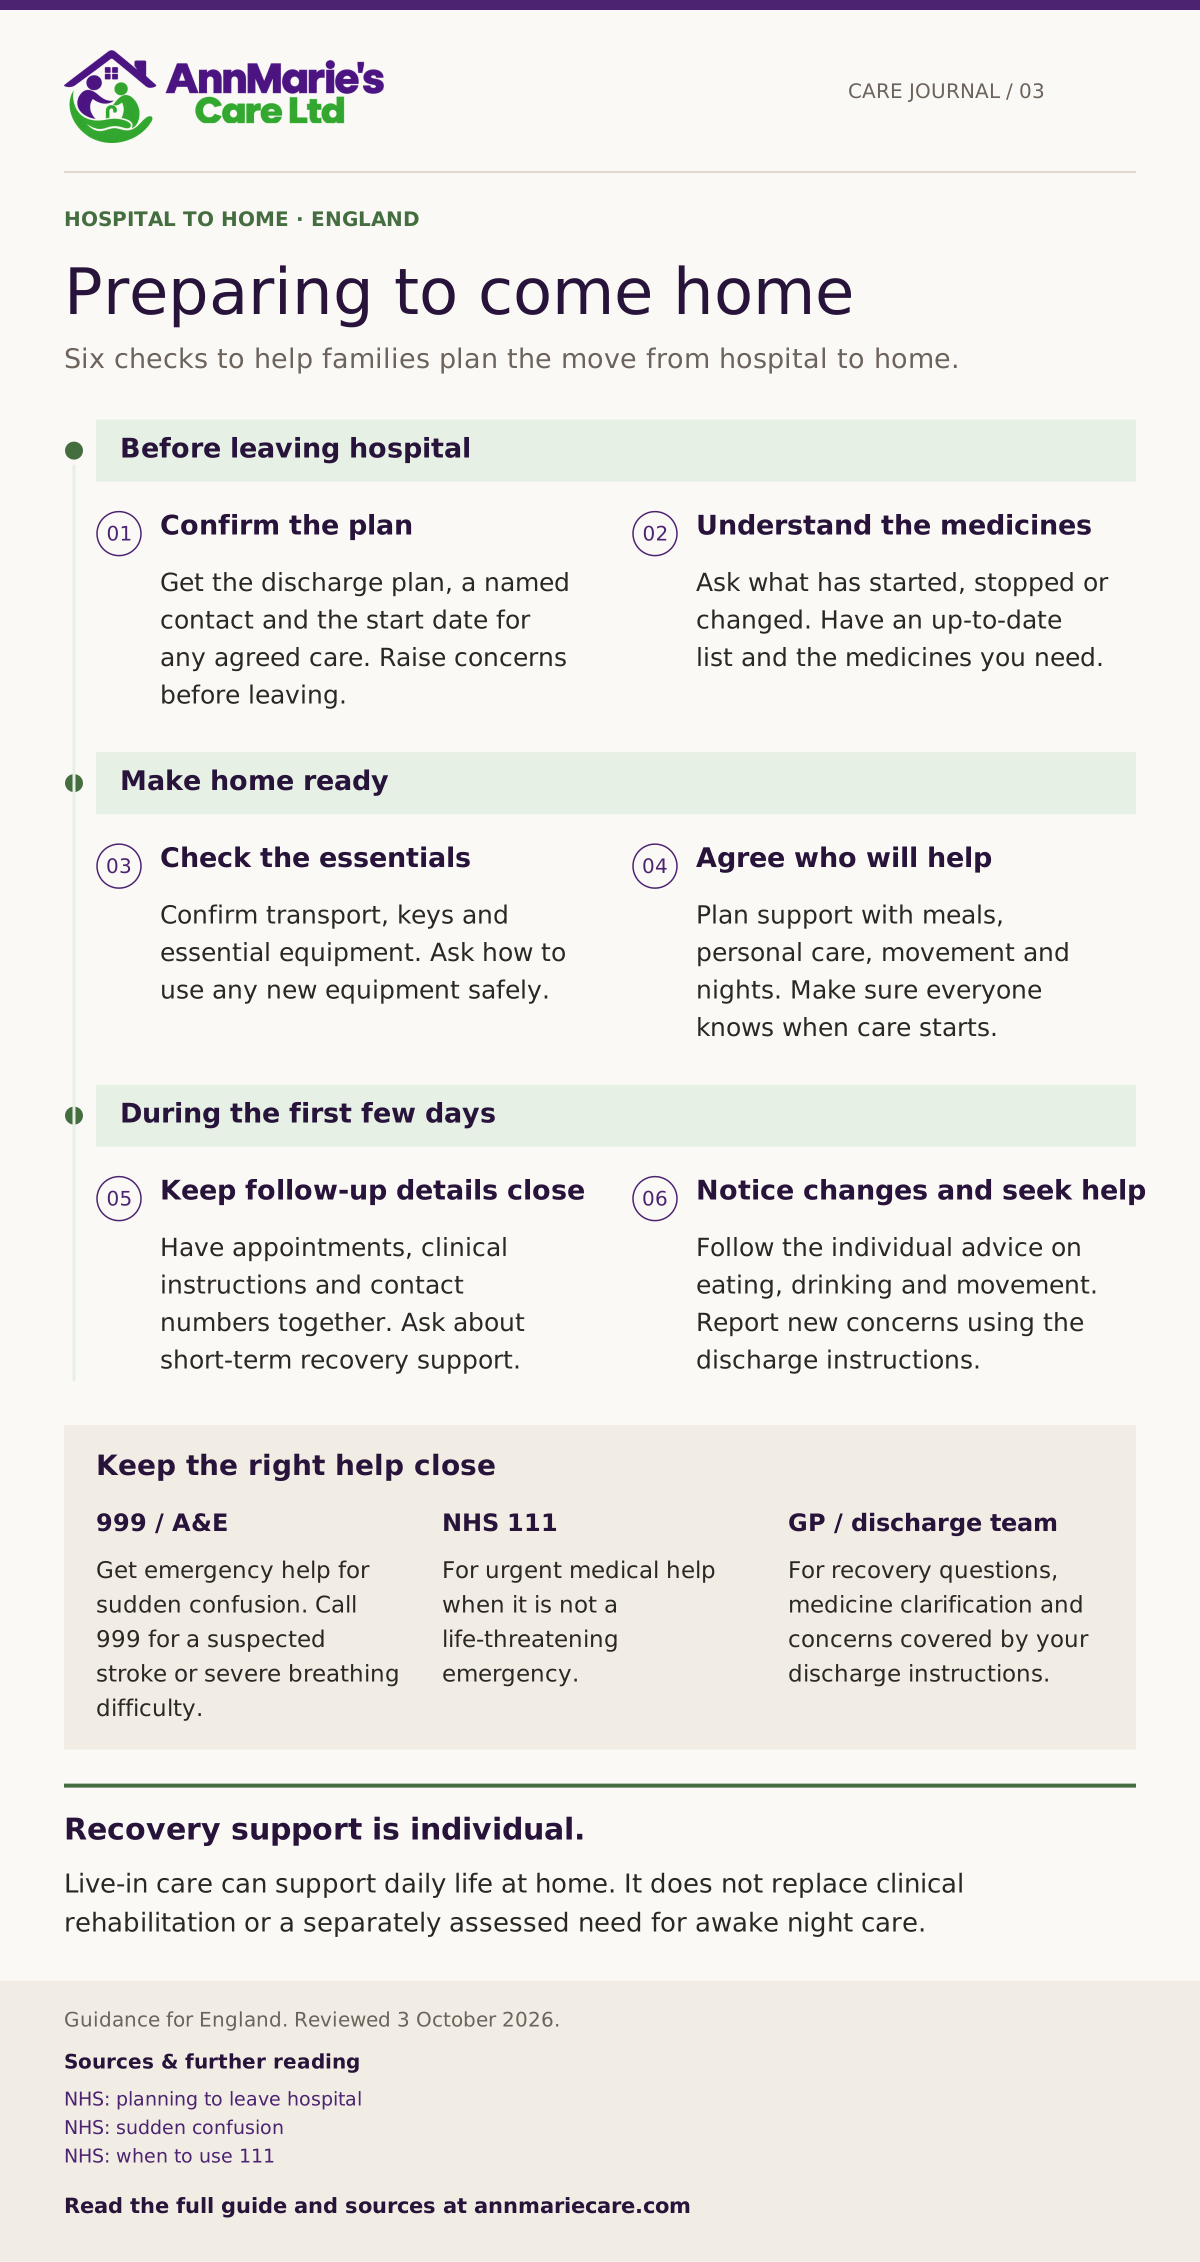
Preparing to come home
Six checks to help families plan the move from hospital to home.
Before leaving hospital
Confirm the plan
Get the discharge plan, a named contact and the start date for any agreed care. Raise concerns before leaving.
Understand the medicines
Ask what has started, stopped or changed. Have an up-to-date list and the medicines you need.
Make home ready
Check the essentials
Confirm transport, keys and essential equipment. Ask how to use any new equipment safely.
Agree who will help
Plan support with meals, personal care, movement and nights. Make sure everyone knows when care starts.
During the first few days
Keep follow-up details close
Have appointments, clinical instructions and contact numbers together. Ask about short-term recovery support.
Notice changes and seek help
Follow the individual advice on eating, drinking and movement. Report new concerns using the discharge instructions.
Before the discharge
Ask for the discharge plan in writing. You are entitled to know what support has been arranged, by whom, and when it starts.
Ask specifically about a reablement package. Many areas provide up to six weeks of free short-term support after a hospital stay. It is not automatic — it has to be arranged, and it is easy to miss.
Check the equipment. If a frame, a commode, a raised toilet seat, a bed rail or a stair rail has been recommended, find out whether it will be delivered before the person is home or three weeks later.
Ask about the medication changes. Doses are very often altered in hospital. Ask what has changed, what has stopped, and what is new — and make sure the GP surgery has the discharge letter.
Check how the house will work now. Ask the occupational therapist or discharge team about stairs, transfers and any temporary downstairs arrangement. Confirm that essential support and equipment will be ready when needed.
The first forty-eight hours
The risks in the first two days are practical ones: a fall in the night, not drinking enough, missing medication, and the exhaustion that follows a hospital stay.
- Somewhere comfortable to sit downstairs, with a phone within reach
- Food that requires no effort at all
- Drinks left where they can be reached without standing up
- A working night light, and a clear path to the bathroom
- Someone who can actually get there quickly if called
What to watch for in the fortnight
Drinks and hydration. Keep suitable drinks within reach and follow the discharge team's advice, especially if fluid intake is restricted or swallowing is difficult. Ask for help if drinking becomes a problem.
Sudden confusion. Go to A&E or call 999 if someone suddenly becomes confused, including a sudden change in someone with dementia. It can have several serious causes; do not assume it is just an infection or ageing.
Eating and appetite. Offer manageable meals that follow the discharge advice. Report poor intake or weight loss, and use prescribed supplements or modified textures as directed by the clinical team.
Movement. Follow the physiotherapist's individual plan, including any restrictions after surgery. Ask for advice if pain, dizziness or fear of falling makes movement difficult; do not push through symptoms.
The wound or the surgical site. Redness spreading, increasing pain, discharge or fever needs medical attention promptly.
Mood. A hospital stay shakes confidence badly. Withdrawal and low mood are common and worth mentioning to the GP.
Who to call
- The discharge team or GP for recovery questions, medication clarification or concerns about a wound, using the instructions you were given
- NHS 111 for urgent help when it is not a life-threatening emergency and you cannot get the advice you need
- 999 for a medical emergency, including sudden confusion, signs of stroke, severe breathing difficulty or suspected heart attack
- Adult social services for a needs assessment, which is free and which you are entitled to request
Where live-in care fits
Short-term live-in care can support an agreed recovery plan through meals, company, assessed medication support and help with appointments. It is separate from clinical rehabilitation. Confirm daily breaks and overnight needs before care begins; a sleeping live-in carer cannot provide continuous awake support.
Many of these arrangements end because they are no longer needed. That is the intended outcome, and a good provider will tell you honestly when they think it can safely stop.
Useful sources
NHS: planning to leave hospital; NHS: support with recovery; NHS: sudden confusion.